
SHORT TERM EFFECTS OF OXYCODONE
INTRODUCTION
Oxycodone is a potent semi-synthetic opioid medication prescribed for the relief of moderate to severe pain that cannot be adequately managed with non-opioid analgesics. As with all opioids, its short-term administration produces a range of predictable pharmacological effects that occur within minutes to hours after dosing. These effects include the desired therapeutic outcome (analgesia) as well as a spectrum of additional physiological and psychological responses that can range from beneficial to uncomfortable or dangerous. Order oxycodone online
Understanding the short-term effects of oxycodone is essential for patients, caregivers, and healthcare providers. Short-term refers here to the period from initial administration through the first few hours to several days of use, before significant tolerance, dependence, or long-term adaptations typically develop. During this window, most of the drug’s acute actions on the central nervous system (CNS), gastrointestinal tract, respiratory system, cardiovascular system, and other organ systems become apparent. Buy oxycodone online without a prescription
This article provides a comprehensive, medically accurate, and neutral examination of the short-term effects of oxycodone. It covers the mechanisms underlying these effects, the expected therapeutic benefits, common and less common side effects, potential serious adverse reactions, factors that influence the intensity and duration of effects, safety considerations during short-term use, frequently asked questions, and a concluding summary. The information is presented in a reader-friendly manner for the general public while remaining grounded in established pharmacological and clinical evidence.
Oxycodone remains a Schedule II controlled substance with substantial risks of misuse, overdose, and life-threatening respiratory depression—even during short-term, medically supervised use. Nothing in this article should be interpreted as medical advice or an endorsement of use outside a licensed prescriber’s direction. buy oxycodone online
PHARMACOKINETIC BASIS FOR SHORT-TERM EFFECTS
ONSET, PEAK, AND DURATION OF ACTION
The time course of oxycodone’s short-term effects is largely determined by its pharmacokinetic profile, which varies by formulation:
- Immediate-release (IR) oxycodone: onset 10–30 minutes, peak plasma concentration 1–2 hours, duration of action 3–6 hours.
- Extended-release (ER) formulations: slower onset (30–60 minutes), peak at 3–4 hours, duration 8–12 hours.
Intravenous administration produces effects within seconds to minutes, while rectal and intramuscular routes fall between oral IR and IV.
These time courses dictate when patients experience peak analgesia, peak side effects, and when effects begin to wane—important information for dosing intervals and breakthrough pain management.
FACTORS INFLUENCING SHORT-TERM EFFECTS
Individual variability in short-term response is influenced by:
- Dose and route of administration
- Opioid tolerance (even short-term prior exposure can blunt effects)
- Age (elderly patients often experience amplified effects)
- Hepatic and renal function (impaired clearance prolongs and intensifies effects)
- CYP2D6 and CYP3A4 genetic polymorphisms (affecting metabolite formation)
- Concomitant medications (especially CNS depressants)
- Body weight and fat distribution
- Food intake (delays absorption of oral forms)
PRIMARY THERAPEUTIC EFFECT: ANALGESIA
MECHANISM OF PAIN RELIEF
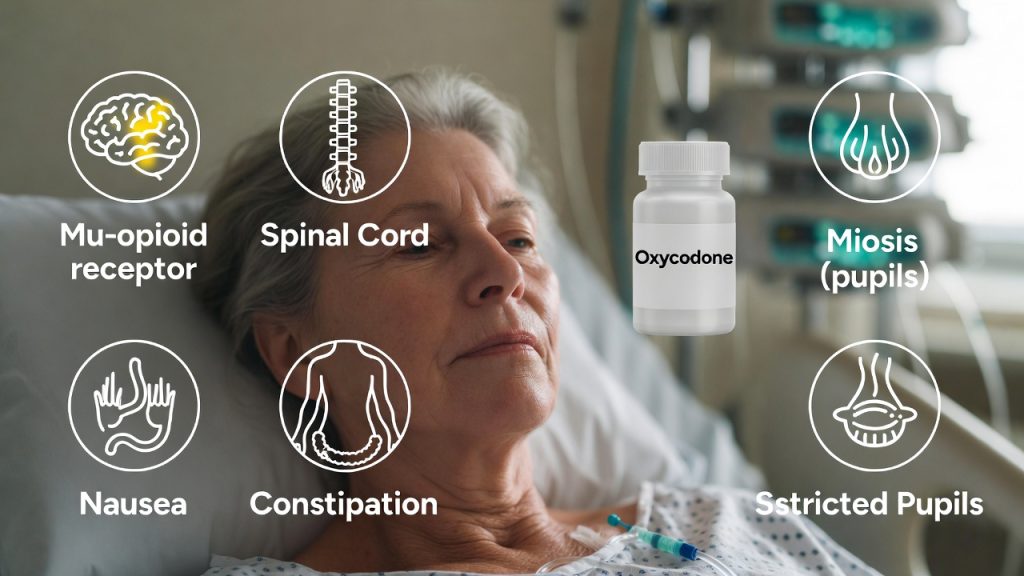
Oxycodone acts primarily as a full agonist at mu-opioid receptors (MOR) in the CNS and, to a lesser extent, peripherally. Binding to presynaptic MOR inhibits release of excitatory neurotransmitters (glutamate, substance P) from primary afferent terminals in the dorsal horn of the spinal cord. Postsynaptic MOR activation hyperpolarizes second-order neurons via opening of GIRK potassium channels and inhibition of voltage-gated calcium channels.
Supraspinally, activation of MOR in the periaqueductal gray and rostral ventromedial medulla recruits descending inhibitory pathways (serotonergic and noradrenergic) that further suppress spinal nociceptive transmission. Limbic and cortical effects reduce the affective component of pain.
ONSET AND QUALITY OF ANALGESIA
Most patients experience noticeable pain reduction within 15–60 minutes of oral IR dosing. The quality of analgesia is often described as “heavy” or “blanketing,” with particular effectiveness against nociceptive (somatic and visceral) pain and variable efficacy against neuropathic pain.
Short-term use typically provides reliable dose-dependent pain relief without rapid tolerance in opioid-naïve individuals.
COMMON SHORT-TERM CENTRAL NERVOUS SYSTEM EFFECTS
SEDATION AND DROWSINESS
Sedation is one of the most frequent short-term effects, resulting from mu-receptor-mediated depression of arousal centers in the brainstem and thalamus. It usually peaks concurrently with peak analgesia and is dose-dependent.
COGNITIVE AND PSYCHOMOTOR IMPAIRMENT
Short-term use commonly impairs attention, reaction time, memory, and coordination. These effects contribute to increased risk of falls (especially in older adults) and motor vehicle accidents.
EUPHORIA AND MOOD CHANGES
In many individuals, particularly at higher initial doses, activation of the mesolimbic dopamine pathway produces euphoria or a sense of well-being. This rewarding effect is a major driver of misuse potential even during short-term exposure.
Dysphoria, anxiety, or emotional blunting can occur in others, particularly those sensitive to kappa-receptor activity or experiencing nausea.
DIZZINESS, VERTIGO, AND LIGHTHEADEDNESS
Orthostatic hypotension and direct vestibular effects contribute to these symptoms, which are more pronounced when standing or changing position rapidly.
RESPIRATORY EFFECTS
RESPIRATORY DEPRESSION
The most serious short-term effect of oxycodone is dose-dependent depression of respiratory drive. Mu-2 receptor activation in the pre-Bötzinger complex and other brainstem respiratory centers reduces responsiveness to hypercapnia and, to a lesser extent, hypoxia.
Clinically significant respiratory depression can occur even at therapeutic doses in opioid-naïve patients, especially when combined with other CNS depressants (benzodiazepines, alcohol, sedating antihistamines, gabapentinoids).
Monitoring for slow/shallow breathing, snoring, or periods of apnea is critical during the first 24–72 hours of therapy or after dose increases.
GASTROINTESTINAL EFFECTS
NAUSEA AND VOMITING
Nausea affects 20–40% of patients during short-term use, primarily due to stimulation of the chemoreceptor trigger zone in the area postrema and delayed gastric emptying.
Vomiting is less common but can occur, particularly with the first few doses.
CONSTIPATION
Opioid-induced constipation results from mu-receptor-mediated reduction in peristalsis, increased non-propulsive contractions, and increased sphincter tone throughout the gastrointestinal tract. It can begin within hours of the first dose and is one of the few opioid side effects that does not rapidly tolerate.
Prophylactic laxatives or stool softeners are often recommended from the outset of short-term therapy.
OTHER COMMON SHORT-TERM EFFECTS
PRURITUS (ITCHING)
Histamine release (not IgE-mediated) from mast cells causes facial and truncal itching in 10–30% of patients. This effect is more common with morphine than oxycodone but still occurs frequently.
MIOSIS (PINPOINT PUPILS)
Pupil constriction results from parasympathetic stimulation via mu-receptor activation in the Edinger-Westphal nucleus. Miosis is a reliable clinical sign of recent opioid exposure.
DRY MOUTH (XEROSTOMIA)
Reduced salivary secretion is common and contributes to dental hygiene challenges even during short courses.
URINARY RETENTION
Mu-receptor activation increases detrusor muscle tone while relaxing the bladder neck, potentially causing difficulty initiating urination or incomplete bladder emptying.
CARDIOVASCULAR EFFECTS
Short-term oxycodone use can produce modest bradycardia and hypotension, particularly with intravenous administration or in volume-depleted patients. Orthostatic changes are common due to sedation and histamine release.
ENDOCRINE AND IMMUNE EFFECTS IN THE SHORT TERM
Although more prominent with chronic use, even short-term administration can transiently suppress luteinizing hormone and testosterone in men and disrupt menstrual cycles in premenopausal women. Minor immunomodulatory effects (reduced natural killer cell activity) have been observed in perioperative settings.
SERIOUS SHORT-TERM ADVERSE EFFECTS
LIFE-THREATENING RESPIRATORY DEPRESSION AND OVERDOSE
Symptoms include profound sedation, cyanosis, slow or irregular respirations (<8–10 breaths/min), coma, and respiratory arrest. Risk is highest during:
- First 24–72 hours of therapy
- Dose escalations
- Combination with other CNS depressants
- Sleep-disordered breathing
- Renal or hepatic impairment
Naloxone is the specific antidote and should be immediately available when oxycodone is prescribed.
ACUTE ALLERGIC REACTIONS
True anaphylaxis is rare but possible. More commonly, histamine-mediated flushing, urticaria, or bronchospasm occurs.
SEIZURES
Very rare in short-term use at therapeutic doses but reported in overdose or in patients with lowered seizure threshold.
FACTORS THAT AMPLIFY SHORT-TERM EFFECTS
- Opioid-naïve status
- Advanced age (>65 years)
- Sleep apnea or obesity hypoventilation syndrome
- Concurrent use of benzodiazepines, alcohol, or other sedatives
- High initial doses or rapid titration
- Intravenous rather than oral administration
SAFETY CONSIDERATIONS FOR SHORT-TERM USE
- Start with the lowest effective dose
- Titrate slowly in opioid-naïve patients
- Avoid or minimize concomitant CNS depressants
- Educate patients and caregivers about signs of overdose
- Co-prescribe naloxone when risk factors are present
- Monitor respiration and sedation level, especially at night
- Use multimodal analgesia to reduce opioid requirements
- Assess for sleep-disordered breathing before initiating therapy
FREQUENTLY ASKED QUESTIONS
- How long do the short-term effects of oxycodone last?
- Why do I feel so sleepy after taking oxycodone?
- Is it normal to feel itchy after the first few doses?
- How can I tell if oxycodone is causing dangerous breathing problems?
- Why does oxycodone cause constipation so quickly?
- Can short-term use of oxycodone lead to addiction?
- Is oxycodone more sedating than other pain medications?
- What should I do if I vomit after taking a dose?
- How soon after taking oxycodone can I drive?
- Why do my pupils get small when I take oxycodone?
CONCLUDING SUMMARY
The short-term effects of oxycodone reflect its primary action as a mu-opioid receptor agonist. Within minutes to hours of administration, patients typically experience meaningful analgesia accompanied by sedation, possible euphoria, nausea, constipation, itching, miosis, and—most critically—dose-dependent respiratory depression.
While short-term use under medical supervision can provide essential pain relief when non-opioid options are inadequate, the same mechanisms responsible for therapeutic benefit also produce serious risks, particularly respiratory compromise. Awareness of the full spectrum of short-term effects, vigilant monitoring, careful dose titration, multimodal analgesia, patient/caregiver education, and ready access to naloxone are essential to maximize benefit and minimize harm during the initial period of oxycodone therapy.
Responsible short-term use requires balancing the legitimate need for pain control against the ever-present potential for life-threatening adverse effects—even when taken exactly as prescribed.